
A weight loss plateau happens when your body adapts to a prolonged calorie deficit, slowing your metabolism and halting progress despite consistent effort. The root cause is metabolic adaptation: as you lose weight, your body burns fewer calories at rest and during activity, eventually matching your reduced intake.
The frustrating part? You’re still doing everything “right.” The scale just stops cooperating. A clinical review of plateau management estimates that roughly 85% of dieters hit one. So if you’ve hit a stall after weeks or months of steady progress, you’re in the overwhelming majority. The question isn’t whether a plateau will happen. It’s what you do when it does.

What Is a Weight Loss Plateau, and When Is It Actually Normal?
A weight loss plateau is generally defined as a period of two or more weeks where the scale doesn’t move despite maintaining your diet and exercise routine. But here’s the nuance most articles skip: not every stall is a true plateau.
Short-term weight fluctuations happen constantly. Water retention from a salty meal, hormonal shifts across your menstrual cycle, or increased glycogen storage after a carb-heavy day can all mask fat loss on the scale. These fluctuations can swing your weight by 2 to 5 pounds in a single day.
True Plateau vs. Normal Weight Fluctuation
A real plateau shows a flat or upward trend over three to four weeks when you’re confident your intake and activity haven’t changed. If your weight bounced up Tuesday and dropped again by Friday, that’s not a plateau. That’s physiology doing its thing.
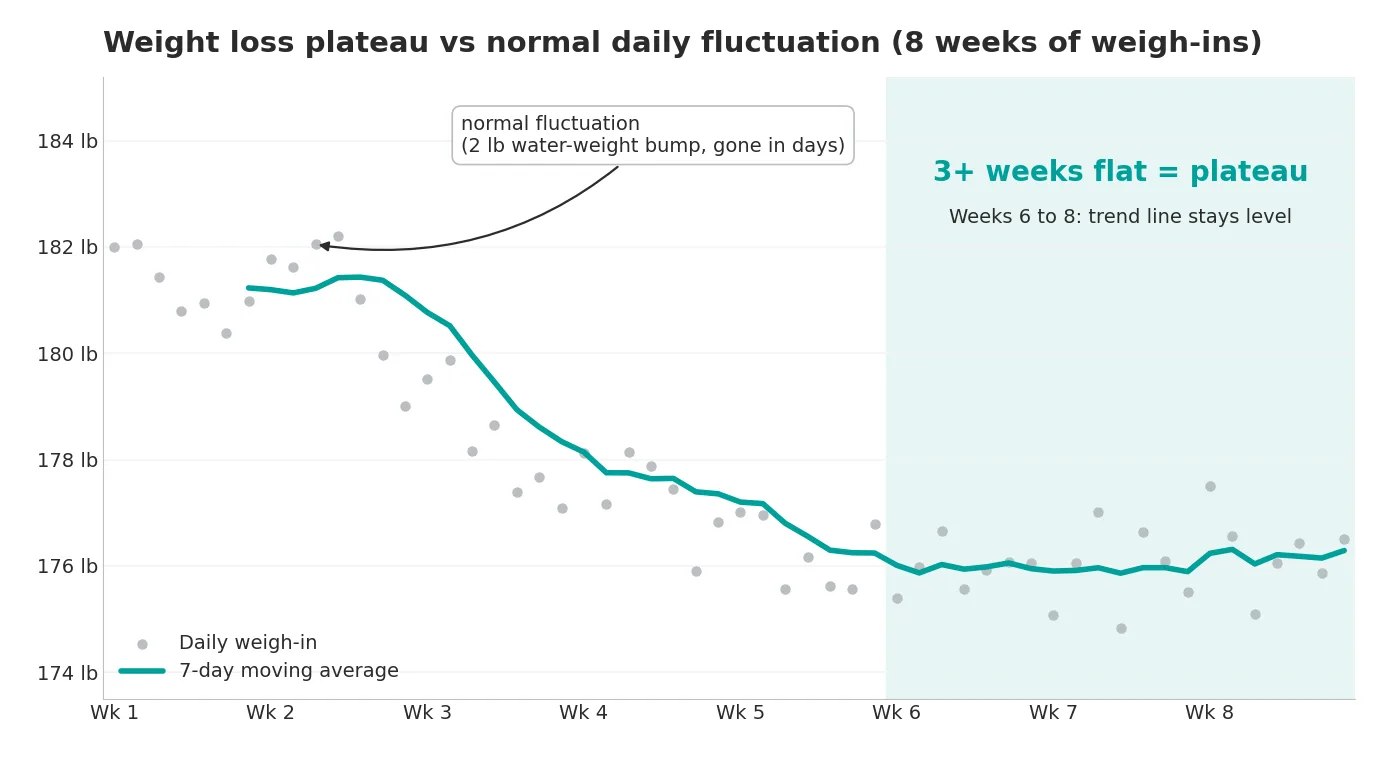
Eight weeks of daily weigh-ins for one person. The gray dots jump around every day; the teal seven-day average is what actually tells you whether you’re losing. The week-two bump is water, gone within days. Weeks six through eight are the real plateau.
The chart above is the whole argument in one picture. Daily weigh-ins are noisy by nature. The seven-day average smooths out the noise, and it’s the only number worth reacting to. When that line has been level for three weeks or more, you’re in a plateau. When it dipped and recovered inside a week, you’re not.
The distinction matters because the response is different. A fluctuation requires patience. A genuine plateau requires a strategy change. Jumping to drastic measures after a few days of stalled weight leads to the kind of extreme restriction that backfires long-term.
Signs You Are Actually in a Plateau
Run through this list. If all five are true, the plan needs to change; if fewer are true, give it another week.
- Three or more weeks flat. Your seven-day average weight has been level or rising for at least three weeks, not just a few bad days.
- Same measurements. Your waist and hip measurements, taken at the same time of day, haven’t moved either.
- Same clothes fit. The waistband that was loosening feels exactly the way it did three weeks ago.
- Tracking is honest. You’ve weighed and logged everything you ate for at least one full week, not estimated it.
- No new medication or life change. Nothing else changed that could explain it: a new prescription, a dose change, a sleep crash, a stressful month, or a shift in your cycle.
How Long Does a Weight Loss Plateau Typically Last?
Most weight-loss plateaus last between two and twelve weeks before responding to a strategy change, and the exact length varies with your starting weight, how aggressive your deficit is, and how consistent your habits have been. For some patients, medically supervised options like peptides for weight loss become part of that strategy change.
A brief one-to-two-week stall usually reflects water and glycogen shifts and doesn’t need intervention. A three-to-four-week plateau despite consistent effort is the point where a strategy adjustment (rather than more restriction) starts paying off. If you’ve been stalled six or more weeks with zero movement on the scale and no change in measurements, that’s a signal to look deeper, often at hormonal factors, thyroid function, or medications that quietly affect metabolism.
Studies of long-term dieters consistently show that everyone plateaus eventually. What separates people who lose the weight for good from those who don’t isn’t avoiding plateaus. It’s how they respond when the scale stops moving.
A stall past three weeks rarely resolves on its own, because intake now matches what a smaller body burns; when progress restarts, about 0.5 to 1 percent of body weight per week is the rate to aim for.
Why Weight Loss Plateaus Happen: The Real Reasons Progress Stalls
Your body doesn’t want to lose weight. That sounds harsh, but from an evolutionary standpoint, your metabolism interprets sustained calorie restriction as a threat. It responds with a coordinated set of adaptations designed to conserve energy and protect your current body composition.
The bigger-picture version is set point theory: your brain defends a preferred weight range and pushes back with more hunger and a lower burn the further you fall below it. A review of body-weight set point models argues the reality is closer to a defended range than a fixed number. Either way, the pushback eases once weight holds steady.
Metabolic Adaptation and Adaptive Thermogenesis
Metabolic adaptation is the single biggest driver behind most plateaus. As you lose weight, your basal metabolic rate drops because a smaller body requires fewer calories to maintain itself. But your metabolism also slows beyond what your new body size alone would predict. This “extra” slowdown, documented in a review of adaptive thermogenesis in humans, is called adaptive thermogenesis.
Your body reduces non-exercise activity thermogenesis (NEAT) as well. You fidget less and move more slowly throughout the day. These invisible reductions can quietly account for hundreds of fewer calories burned each day, enough to erase a moderate calorie deficit entirely.
Muscle Loss and Hormone Changes
When you lose weight in a calorie deficit, you don’t just lose fat. Some of that loss comes from lean muscle tissue, especially if you’re not strength training or eating adequate protein. Since muscle is more metabolically active than fat, losing it further lowers your calorie burn at rest.
Hormonal changes compound the problem. Leptin, the hormone that signals fullness to your brain, drops as body fat decreases. Meanwhile, ghrelin, the hunger hormone, increases. Thyroid hormones can also downregulate, slowing your metabolic rate further. For many adults over 40, these hormonal shifts overlap with age-related changes that make plateaus feel especially stubborn. Understanding the connection between weight loss with a hormone imbalance is often the missing piece in the puzzle. If you’re a woman noticing this pattern around perimenopause, the crossover with low estrogen symptoms often shows up on the scale before anywhere else, and a comparison of BHRT vs HRT options can help you have a more informed conversation with your provider.

Calorie Creep and Adherence Drift
This one stings a little, but it’s worth an honest look. A controlled study of self-reported intake found that people underestimate calorie intake by roughly 30 to 50 percent, even when they believe they’re tracking carefully. Portion sizes gradually increase. Cooking oils get a heavier pour. A few bites here and there go unlogged.
None of this means you’re failing. It means you’re human. But after months of dieting, these small drifts accumulate and can quietly close the gap between your intake and your (now lower) energy expenditure.
How to Break Through a Weight Loss Plateau Without Extreme Dieting
The worst thing you can do at a plateau is slash calories further. Dropping to 1,000 or 1,200 calories accelerates muscle loss, tanks your energy, and deepens the metabolic adaptation you’re trying to overcome. A smarter approach targets the root causes instead.
Prioritize Strength Training Over More Cardio
If you’ve been relying on cardio to drive your deficit, this is the single most impactful change you can make. Resistance training preserves and builds lean muscle, which directly supports your resting metabolic rate. Two to three sessions per week focused on compound movements will do more for plateau-breaking than adding another hour on the treadmill.
Body recomposition (losing fat while maintaining or gaining muscle) sometimes means the scale stays flat even though your body is visibly changing. Measurements and how your clothes fit often tell a more accurate story than your weight alone.

Consider a Strategic Diet Break or Refeed
This sounds counterintuitive, but temporarily increasing your calorie intake to maintenance level for one to two weeks can help reset some of the hormonal adaptations driving your plateau. A planned diet break isn’t the same as “falling off the wagon.” It’s a deliberate strategy, and it lines up with what behavior-change research on habits finds more broadly: small structural changes to routine and environment tend to outperform white-knuckle willpower when a plan has stopped delivering.
A refeed day, typically one day per week at maintenance calories with an emphasis on carbohydrates, offers a shorter-term version. Higher carb intake temporarily boosts leptin levels and can improve training performance during your next week of dieting.
Sleep Quality, Stress, and Food Quality
Poor sleep alone can stall weight loss. Even modest sleep deprivation (six hours instead of seven or eight) increases cortisol and ghrelin while reducing insulin sensitivity, according to a review of sleep restriction and appetite. If your sleep has deteriorated since you started dieting, address that before changing anything else.
Chronic stress creates a similar hormonal environment. Elevated cortisol promotes water retention and encourages fat storage around the midsection. Stress management isn’t a soft recommendation here. It’s a physiological intervention.
Food quality matters beyond the calorie count, too. Ultra-processed foods can drive overeating through mechanisms that calorie tracking alone doesn’t capture. Shifting toward whole foods with higher protein and fiber content improves satiety and often reduces intake naturally without requiring a stricter calorie target.
Protein and Fiber Targets
A review of protein and weight management puts the useful range at 1.2 to 1.6 grams of protein per kilogram of body weight per day. Fiber matters almost as much: in a calorie-restricted diet study of fiber intake, fiber was the strongest single predictor of weight lost, so aim for 25 to 30 grams a day for most women and 30 to 38 for most men.
Audit Your Tracking Honestly
Spend one week weighing every single thing you eat. Not estimating. Weighing. Most people who do this after months of “eyeballing” portions discover a significant gap between perceived and actual intake. This isn’t about obsessive tracking forever. It’s a diagnostic tool to identify where calorie creep may have crept in.
Recalculate Your Caloric Needs at Your New Weight
Weight loss changes your energy needs. Once you’ve dropped 10 to 15 percent of your starting body weight, your maintenance calories can fall by roughly 200 to 300 per day (sometimes more) compared to your original baseline. That means the same intake that used to create a deficit now equals maintenance, and the scale stops moving.
Recalculate your target every 10 to 15 pounds lost using a validated equation like Mifflin-St Jeor, then subtract 15 to 20 percent for a modest deficit. Adding a few hundred non-exercise steps or one extra short strength session is often easier and more sustainable than cutting more food.
Try Intermittent Fasting or Calorie Cycling
If you’ve been eating the same calorie target every day for months, your body has fully adapted. Introducing variability can shake the system out of its steady-state adaptation. Two evidence-informed approaches:
- Intermittent fasting. 16:8 (eating window from noon to 8pm) or 18:6 approaches, or one 24-hour fast per week. Works primarily by reducing overall intake without forcing constant restriction.
- Calorie cycling, higher intake on training days, lower on rest days, keeping the weekly average in a modest deficit. Helps preserve training performance while creating variability.
Neither approach is magic. Both work when they help you eat less overall without feeling perpetually restricted. Fasting isn’t appropriate if you have a history of disordered eating, are pregnant, are underweight, or take medications that require food. Talk to your provider before trying it.
Track Beyond the Scale: Metrics That Actually Show Progress
Scale weight is one signal, and it’s often not the most useful one at a plateau. Body composition can shift meaningfully even when weight holds steady. Watch several data points instead of just the number on the scale:
- Waist and hip measurements, taken weekly at the same time of day
- Progress photos (front, side, back) every 2 to 4 weeks in the same lighting and same clothes
- Strength progression in the gym, heavier weights, more reps, or shorter rest between sets
- How your clothes fit, particularly waistbands and tighter items you already own
- Resting heart rate and sleep quality trends
- Energy, mood, and hunger consistency across the week
If the scale hasn’t moved but your waist dropped an inch, your lifts went up, and your morning pants fit better, you’re losing fat and gaining muscle. That’s a win the scale can’t measure. Body recomposition often stalls scale weight for weeks while measurable body changes accumulate underneath.
When a Plateau Means It’s Time for Medical Support
Lifestyle adjustments solve most plateaus. But not all of them. Here’s a simple decision framework based on how long you’ve been stalled with consistent effort:
- Week 1–2 stall: Normal. Keep going. Usually water and glycogen shifts.
- Week 3–4 stall: Time for a strategy change. Add strength training, recalculate calories, or try a diet break at maintenance.
- Week 5–6 stall: Self-audit your tracking (weigh everything for one week), check sleep quality, and look for hidden stress or lifestyle drift.
- Week 6+ stall despite consistent effort: Time for bloodwork and a medical evaluation. Something structural may be at play.
If you’ve been consistent with your nutrition, training, and sleep for six or more weeks with zero movement on the scale or in measurements, something deeper may be at play.
Certain red flags warrant professional evaluation rather than more self-directed troubleshooting:
- Persistent fatigue that doesn’t improve with better sleep
- Hair thinning or feeling cold all the time (possible thyroid dysfunction)
- Irregular menstrual cycles or severe PMS symptoms
- Inability to lose weight despite a verified calorie deficit below your calculated needs
- Age-related changes in body composition, especially after 40
These symptoms may point to hormonal imbalances that no amount of meal prep or gym sessions will fix on their own. Adults navigating perimenopause, menopause, or declining testosterone levels often hit walls that require clinical support to move past. For those wondering whether hormonal factors are relevant, hormone therapy evaluation provides clarity on what’s actually happening inside your body.

Female Weight Loss Plateau: Perimenopause, Thyroid, and PCOS
Women plateau for every reason above, plus three that show on blood work.
Perimenopause. In a SWAN body-composition study, fat gain roughly doubled at the start of perimenopause while lean mass began to decline.
Thyroid. An underactive thyroid slows resting metabolism; a clinical overview of hypothyroidism notes TSH is the standard first test.
PCOS. A review of insulin resistance in PCOS puts it at 50 to 70 percent of affected women.

The Coastal team at the women’s wellness clinic in Jacksonville.
At Coastal, the women’s wellness clinic in Jacksonville starts with blood work, and where results point to low estrogen, progesterone, or testosterone, Dr. Olivia, DNP, APRN, tailors BHRT in Jacksonville to those results and monitors it.
Medical Weight Loss Options That Address the Root Cause
Medical weight loss isn’t about shortcuts. It’s about identifying and treating the specific biological factors that lifestyle changes alone can’t override. The best programs start with data, not prescriptions.

A Coastal patient’s medical weight loss in Jacksonville before and after. Individual results vary.
Comprehensive Hormone Testing Comes First
At Coastal Health & Medical Spa in Jacksonville, the process begins with lab work and a medical history review before any medication is considered. Dr. Olivia, DNP, APRN, uses that lab work to see whether your plateau has a hormonal component or whether a refined lifestyle strategy is the better path forward.
That distinction matters. Not every stalled scale reading is a hormone problem, and prescribing medication without knowing your baseline levels is guesswork, not medicine.
GLP-1 Receptor Agonists for Chronic Weight Management
For patients who meet clinical criteria, FDA-approved GLP-1 receptor agonists like semaglutide and tirzepatide have shown significant efficacy for chronic weight management. These medications work by regulating appetite signals and improving insulin sensitivity, directly addressing the hormonal hunger amplification that makes plateaus feel impossible to break through willpower alone.
Through Coastal’s medical weight loss program in Jacksonville, patients receive custom-tailored injectable and oral medications with 30-day supplies shipped directly to their door, with in-person or telehealth follow-up. Nutritionist referrals are available on request, because medication works best alongside the lifestyle fundamentals, not as a replacement for them.
If you only have a small amount to lose, fit depends on clinical criteria and medical history, not the number of pounds.
Peptide Therapy as a Complementary Approach
Some patients benefit from peptide therapy as part of a broader metabolic support strategy. While specific peptides like sermorelin are not FDA-approved for weight management, they may support related goals under clinical supervision. Dr. Olivia evaluates whether peptide protocols are appropriate based on individual lab results and health history. If the term is new to you, start with our explainer on what peptides are and how they signal the body.
Weight Loss Plateau on Semaglutide or Tirzepatide
You’re between dose steps. Both medications are stepped up gradually, a schedule the FDA approval notice for tirzepatide describes as part of the label, and the scale often stalls until the next step. That’s expected, not a reason to change your dose on your own.
You’ve reached the medication’s plateau. In the 68-week semaglutide trial, average loss reached about 15 percent of body weight and the slope flattened in the second half, which is the medication holding a new set point. The 72-week tirzepatide trial shows the same flattening after month nine.
You’ve lost muscle along with fat. A smaller appetite makes it easy to under-eat protein, so the targets above matter even more here.

Dr. Olivia, DNP, APRN, reviewing a patient’s medical weight loss plan at Coastal.
At Coastal, Dr. Olivia, DNP, APRN, reviews your dosing schedule, intake, training, and labs, and adjusts the plan within the label.
How to Keep the Weight Off After Breaking Through
Breaking a plateau is only half the battle. Maintaining your new weight requires a deliberate transition out of the deficit phase. Jumping straight to unrestricted eating after months of dieting is the fastest route to regain.
A reverse dieting approach, where you gradually add calories back (many coaches recommend increments of roughly 50 to 100 per week) until you reach maintenance, gives your metabolism time to adjust upward without triggering rapid fat storage. Continuing strength training protects the lean mass that keeps your metabolic rate healthy long-term.
Regular check-ins (whether self-directed or with a provider) catch small drifts before they become major setbacks. Weighing yourself weekly and tracking trends over time keeps you honest without creating daily anxiety over normal fluctuations.
Your Plateau Has a Cause, and It Has a Solution

Dr. Olivia, DNP, APRN, during a weight loss consultation in Jacksonville.
A weight loss plateau doesn’t mean your body is broken or that your effort has been wasted. It means your body has adapted, and your approach needs to evolve with it. For many people, the strategies outlined above are enough to restart progress within a few weeks.
But if you’ve been stuck for more than a month despite consistent effort, or if you suspect hormonal factors are working against you, guessing isn’t a strategy. Schedule a consultation with Dr. Olivia, DNP, APRN, at Coastal Health & Medical Spa in Jacksonville to get lab work and a personalized weight loss plan built around your biology, not generic advice. Book your consultation today, learn more about the Coastal team, or reach our Jacksonville office to find out exactly what’s standing between you and your next breakthrough.
Frequently Asked Questions
How to break a plateau on weight loss?
Usually not by eating less. Cutting calories further accelerates muscle loss and deepens metabolic adaptation. Start with two to three strength sessions a week, a protein target of 1.2 to 1.6 grams per kilogram, better sleep, and a short diet break at maintenance. If nothing moves in six weeks, get labs.
How to shock your body out of a plateau?
You can’t shock it, but you can change the signal. A one-to-two-week diet break at maintenance calories, a switch from steady cardio to progressive strength training, or calorie cycling between training and rest days gives your body a different input to adapt to. Crash dieting and marathon cardio usually deepen the stall.
Is it normal to experience a 3-week weight loss plateau?
Yes. Three weeks is where a stall stops being water and glycogen noise and becomes a real plateau. Your body adapts to a prolonged deficit: basal metabolic rate falls, non-exercise movement decreases, appetite hormones shift, and small tracking drifts erode the deficit until your intake matches your new, lower energy needs.
How long should a plateau last in weight loss?
A true plateau typically lasts 2 to 4 weeks before it responds to a strategy change. If the scale hasn’t moved in 6 or more weeks despite consistent nutrition, training, and sleep, that’s a signal to reassess with a provider, especially if hormonal symptoms are present.
